📅 Book an Appointment

Breaking the Cycle: Why Avoidance Behaviours Lead to More Avoidance


A person sitting alone in a row of empty chairs in a quiet clinic waiting area

Anxiety can be an uncomfortable and distressing feeling that we want to get rid of. This can lead to making choices that will alleviate our anxiety in the quickest way. Avoidance behaviours can encompass a wide range of physical and mental actions, from procrastination and refusing to think about certain things, to social withdrawal and distracting oneself. These behaviours can momentarily ease discomfort but ultimately reinforce the problems they are meant to alleviate.

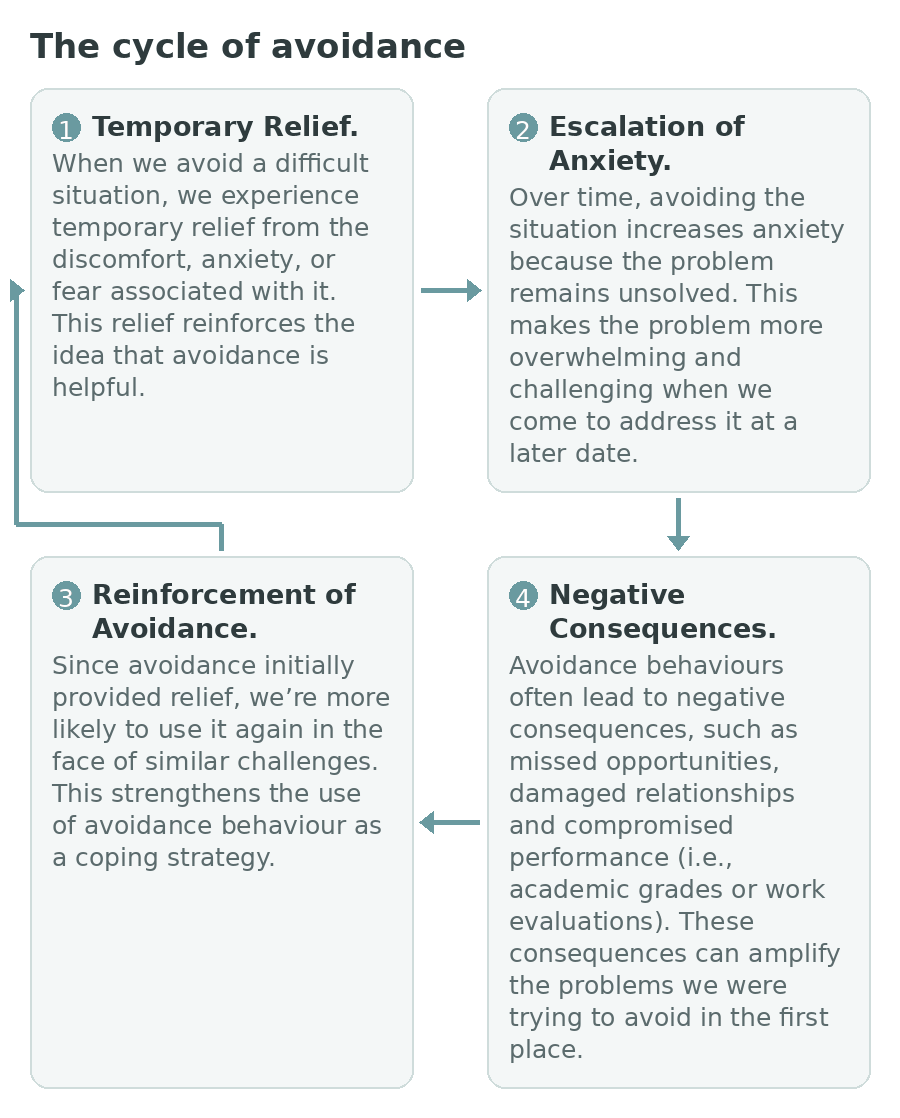
Here’s how the cycle of avoidance typically unfolds:

  1. Temporary Relief. When we avoid a difficult situation, we experience temporary relief from the discomfort, anxiety, or fear associated with it. This relief reinforces the idea that avoidance is helpful.
  2. Escalation of Anxiety. Over time, avoiding the situation increases anxiety because the problem remains unsolved. This makes the problem more overwhelming and challenging when we come to address it at a later date.
  3. Reinforcement of Avoidance. Since avoidance initially provided relief, we’re more likely to use it again in the face of similar challenges. This strengthens the use of avoidance behaviour as a coping strategy.
  4. Negative Consequences. Avoidance behaviours often lead to negative consequences, such as missed opportunities, damaged relationships and compromised performance (i.e., academic grades or work evaluations). These consequences can amplify the problems we were trying to avoid in the first place.
A four-stage loop showing how avoidance repeats: temporary relief, escalation of anxiety, reinforcement of avoidance and negative consequences, returning to the start
Four strategies for breaking the cycle of avoidance: seek support, mindfulness, problem-solving and self-compassion

Breaking the Cycle

Breaking the cycle of avoidance can seem daunting and overwhelming. However, gradually taking steps towards confronting feared situations will go a long way in breaking down this cycle and building a sense of confidence. While it may be tempting to jump into the deep-end and tackle your biggest fear first, taking a slow and persistent approach allows for you to learn and practise skills that can assist you.

  1. Seek Support. Reach out to friends, family, or professionals for support when dealing with challenging situations or emotions. Having a support network can make it easier to confront problems.
  2. Mindfulness. Practising mindfulness helps keep us in the present and stops us catastrophising about hypothetical outcomes.
  3. Problem-Solving. Instead of avoiding problems altogether, break them down into more manageable steps. Create an action plan to assist with tackling these steps.
  4. Self-Compassion. Be kind to yourself. Avoid self-criticism, and recognise that there may be set-backs. Self-compassion can reduce the fear associated with confronting difficulties.

Avoidance behaviours may offer temporary relief, but they are ultimately counterproductive, fuelling a cycle of increased avoidance. To break this pattern, it’s vital to confront challenges directly and adopt healthier coping strategies. By doing so, we can not only avoid the negative consequences of avoidance but also experience personal growth and resilience.

Simone Chaochalakorn smiling in a headshot

Our Blog Author
This post was written by Simone Chaochalakorn, formerly a Psychologist at Your Mind Matters. Support for anxiety and avoidance continues to be part of our services. Meet our team.


📅 Book an appointment

Assertiveness: What does it look like and why it’s important

A scatter of blank wooden letter tiles on a table, with a person sitting further back out of focus

Most people have experienced situations where they have not received what they wanted or needed. These might have been at work, with friends, family, or in intimate relationships. Some may have thought “I am just not an assertive person” and let it go or potentially have it fester into ongoing resentment or sense of helplessness. Some, may have reacted in an opposite manner, with anger and frustration, but this too did not result in needs being met but rather fractured relationships.

Assertiveness is important in all spheres of life from domestic to social to vocational. If you have ever found it difficult to get your point across, to even speak up or keep your cool and had a difficult time communicating your needs, you will undoubtedly recognise the importance of assertive communication in balancing relationships and having needs met.

Diagram listing nine traits of assertive communicators, numbered from direct eye contact to positive, proactive and precise communication

Whilst one might accept these circumstances as the norm of not being assertive, assertiveness is actually a set of skills that can be learned and developed. Personality, culture, life experiences and previous relationships may all make this skill harder to learn for some people, however it is possible to learn to be assertive and doing so is likely to make a positive difference to one’s life.

So what is Assertiveness and what is it not?

Although the meaning of “assertive” may be familiar, it is important to consider what Assertive Communication actually looks like and what it entails.

Assertive communication has been defined as “the ability to speak and interact in a manner that considers and respects the rights and opinions of others while also standing up for your rights, needs, and personal boundaries” (Pipas & Jaradat, 2010, pp. 649). In other words, it’s a communication style which is comprised of direct yet calm, respectful and reasonable expression of your needs whilst also taking the other party’s needs into account. It is standing up for your values without impeding another’s right to do so. Assertiveness is a key skill that can help you to better manage yourself, people and situations. It can help you to influence others in order to gain acceptance, agreement or behaviour change whilst allowing one to feel less guilty for saying ‘no’ to tasks or plans that may not be serving them. It is not coming out as the champion of a heated argument. Assertiveness is knowing when and how to demonstrate your view.

Conceptually, if we look at communication styles on a continuum, assertiveness is the middle balance between being passive (where one is overly focussed on the needs of others’, but struggles to vocalise their own) and being aggressive (where a person may be overly forthright and demanding about their needs, but fail to acknowledge the needs and wants of others). Assertiveness is therefore a positive personality characteristic that enables individuals to be present, actively engaged and aware of their rights, whilst also extending the same to others. They are a benefit to both themselves and society (Parmaksiz, 2019).

Benefits of Assertiveness vs Consequences of when it’s lacking

The importance of feeling considered, heard and valued is well established. Not having our reasonable needs or wants met and feeling that these are not seen as important or valued, leads to feelings of stress and upset. These negative emotions can compound over time and can become a “time bomb” with detrimental impacts on our self-esteem, anxiety and stress (Bulantika and Sari, 2019). A lack of assertiveness may contribute to depression and anxiety, whereas maladaptive approaches to assertiveness may manifest as aggression (American Psychological Association, n.d.a, para. 1).

What are some of the traits of Assertive Communicators?

There are certain traits that are present in effective assertive communication, spanning both verbal and non-verbal characteristics.

  1. Direct eye contact which communicates confidence and that the person is not intimidated
  2. Assertive posture/stance which balances an open confident stance without looking aggressive. Hand gestures and fidgeting also need to be minimised.
  3. Tone of voice should be confident, strong, but not loud and aggressive.
  4. Clarity of communication is vital, so using specific words that clearly communicate ones needs with little room for ambivalence can assist in getting the message across.
  5. Facial expression needs to remain calm and important to not express anger or anxiety.
  6. Timing of any conversations needs to be considered and appropriate as should the audience
  7. Non-threatening: the person should not blame or threaten the others in order to get their way.
  8. Ability to own your mistakes whilst not taking the ownership for the mistakes of others is part of standing up for own beliefs.
  9. Communication needs to be framed in a positive, proactive but precise manner and self-criticism should be avoided when trying to be assertive. It’s imperative that when trying to have effective communication, you’re clear on your position and needs.

While assertive communication skills come naturally for some individuals, these skills can be developed through practice. Effective communication can assist career progression and improve relationships. Relationships are complex and individual and sometimes we may need additional support navigating them. Psychological therapy can be helpful to develop skills in assertiveness in a safe supportive space. If you would like some support with better managing communication and improving the quality of interactions, why not give us a call today? Our team of highly skilled and well-experienced practitioners are here to help.

References

  • American Psychological Association (n.d.a). Assertiveness. In APA Dictionary of Psychology. APA Dictionary of Psychology
  • Bishop, S. (2013). Develop your assertiveness. London, UK: Kogan Page Limited.
  • Bulantika, S. Z., & Sari, P. (2019). The effectiveness of assertive training techniques and thought-stopping techniques to increase student assertiveness ability. Biblio Couns: Jurnal Kajian Konseling dan Pendidikan, 2(3), 109–116.
  • Millacci, T. (2017). Assertiveness in the Workplace: A Quick Guide. Assertiveness in the Workplace
  • Pipaş, M., & Jaradat, M. (2010). Assertive communication skills. Annales Universitatis Apulensis Series Oeconomica, 12, 649–656.
  • Williams, M. (2023). What is Assertiveness and why it is important. What is Assertiveness and why is it important
Diagram of the continuum of communication styles, with passive at one end, aggressive at the other and assertive as the middle balance
Lana Lubomirska wearing glasses, in a portrait photograph

Our Blog Author
This post was written by Lana Lubomirska, Senior Psychologist at Your Mind Matters. Lana works with children, adolescents and adults from a range of cultural and socioeconomic backgrounds, and is committed to providing a client-centred, safe environment for every individual. Meet our team.

Book an appointment

Coping with the Stress of Year 12’s Final Semester with Strategies for Success

A person stepping back from a small calm dog whose shadow looms over the scene, far larger than the animal itself

People can be scared of many different things, such as dogs, aeroplanes, needles or insects. And the degree to which we’re fearful of these things can also vary. For example, I personally am scared of birds (this is also known as ornithophobia). Yes, I know…terrifying. However, it’s a mild fear, as this does not stop me from walking through a park where I know birds will be present, or walking down the sidewalk when I see them on the footpath in front of me. I may not like it, but it doesn’t interfere with my life. Unfortunately, this may not be the case for everyone, because, as mentioned above, the degrees of fear can vary. Many individuals will go out of their way to avoid that which causes fear. Some may never go on a desired holiday, or see family interstate due to being frightened of flying. Others may avoid going outside in spring and summer due to their fear of bugs. In these circumstances, seeing a psychologist can be helpful, in order to help tackle this issue.

Systematic desensitisation: building a hierarchy, working through it step by step, and what supports each step

One way to do this, and my preferred way, is through systematic desensitisation. This involves gradual exposure to that which causes fear and discomfort. To start off, I work with my clients to develop a hierarchy, starting with what causes the least amount of fear, or anxiety, and building up to that which causes the most fear. It’s important that clients follow these steps in an environment that is safe and predictable. Let’s use fear of dogs as an example. Depending on the severity, step one may be just talking about dogs. Believe it or not, this alone can be enough to cause uneasy feelings for some. I ask my client to rate their anxiety level for step one (1-10). The idea is that the more the client is exposed to this step, they will become desensitised, leading to their self-rating to drop over time. Once the client is comfortable and essentially bored with this step, we then move onto step two. Step two may involve looking at pictures of dogs. For example, I would advise against going to a dog park to observe dogs there, as this is an unpredictable environment, as we cannot control or stop a dog from running up to the client, which could lead to more distress. Moving on, step three may involve looking at videos of dogs. Once again, the client would continue to rate their level of discomfort, and eventually, once this drops to an extremely comfortable level, we move on to the next step. Eventually, the aim and goal would be to have the client comfortably sitting in a room with the dog, and even interact with a dog.

In addition to a hierarchy, it is beneficial to work on breathing strategies in sessions as well. These help ease some of the discomfort within each step. Learning to challenge unhelpful and unrealistic thoughts via CBT (Cognitive Behavioural Therapy) is also very helpful, as often, we overestimate the level of threat, and are more fearful of certain things than necessary.

Luna, a yellow Labrador Retriever, sitting on the grass wearing a blue therapy dog vest

Animal-assisted therapy for animal-related fears

If an individual has an animal-related fear, such as the above, it can be beneficial if the psychologist they are working with utilises animal-assisted therapy. Therapy dogs are generally quite well-trained and love people. Exposure to therapy animals is done in a safe and predictable environment, and it’s reassuring to know that the specific dog is friendly, and that the handler (in this case, the therapist), has an understanding of the client’s fear, and can work with the client in a manner in which they are comfortable. As opposed to attempting to interact with a dog at a dog park, or on the street, which is less predictable. However, it is important to ensure that the psychologist and therapy animal you choose to work with are suitable for your own level of fear, as some dogs can be more excitable than others and may not be suitable for someone who has trouble even being in the same room as a dog.

Luna in her therapy dog vest.

If you think working with a psychologist would help you tackle your fear, give us a call to find a psychologist that is suitable for you. Please note that Johana is able to assist with clients who have a moderate fear of dogs, as Luna is an excitable dog.

Johana Xanthopoulos with her therapy dog Luna

Our Blog Author
This post was written by Johana Xanthopoulos, Clinical Psychologist at Your Mind Matters. Johana works with children and adolescents, with particular experience in autism, anxiety and depression, and has completed Animal Assisted Therapy training with her dog Luna. She is fluent in English and Greek. Meet our team.

Book an appointment

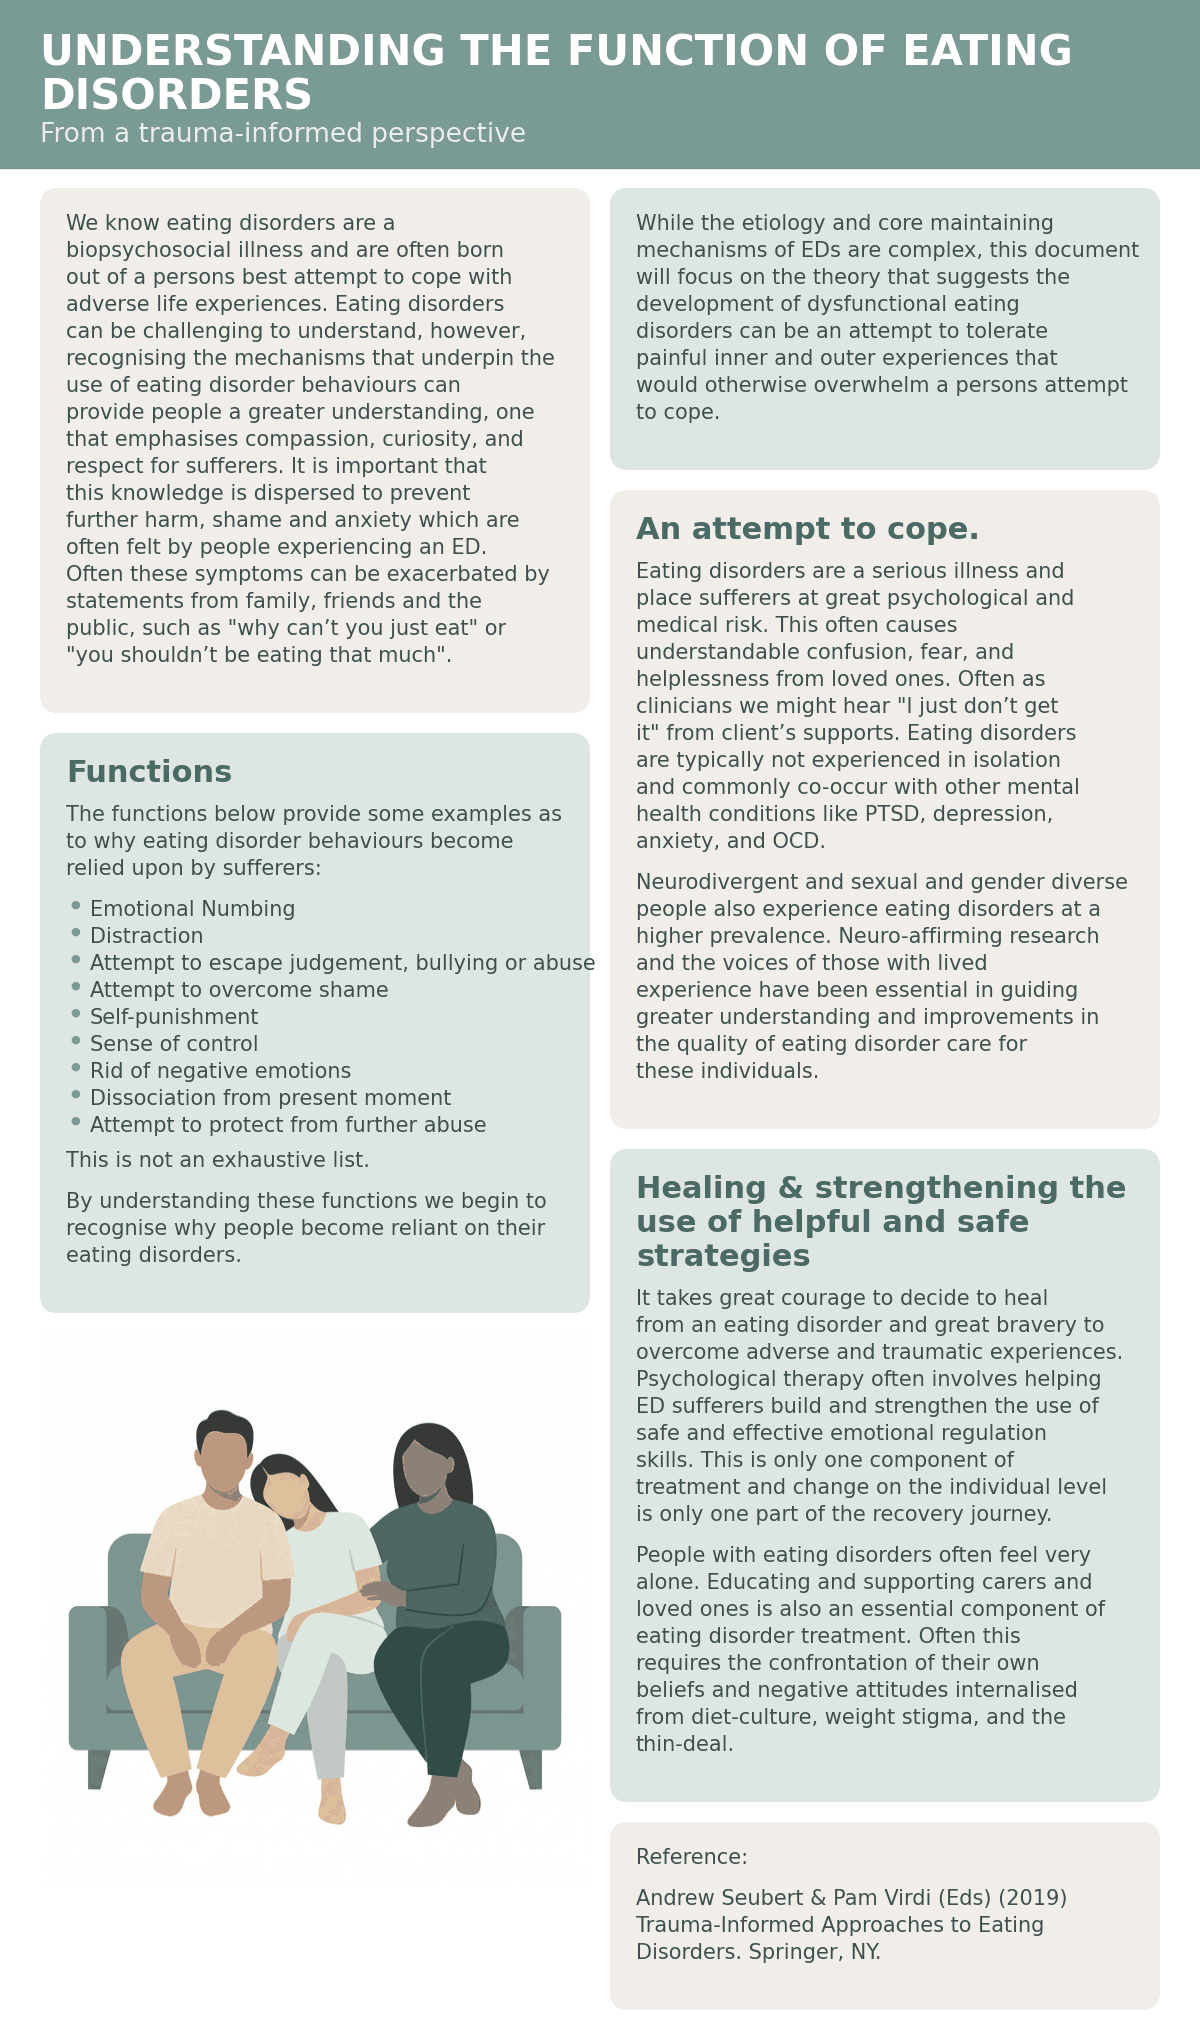
Understanding the function of an eating disorder (Infographic)

Please note: the following infographic has been designed to help readers better understand eating disorders and why some are so difficult to manage. Each case is different, and requires tailored intervention. However, if you’ve ever wondered why someone may develop an eating disorder, and struggle to free themselves from it, this may provide some insight.

Infographic titled Understanding the function of eating disorders, from a trauma-informed perspective, setting out why eating disorder behaviours are relied upon and how healing works

If you need support right now

If this is an emergency, call 000. For 24-hour crisis support, call Lifeline on 13 11 14 or text 0477 13 11 14.

For eating disorder support, the Butterfly National Helpline is available on 1800 33 4673, seven days a week from 8am to midnight, except on national public holidays. Butterfly is a support line rather than a crisis line. More options are on our resources page.

Blair Raatjes smiling, in front of a wall with a hanging plant

Our Blog Author
This infographic was created by Blair Raatjes, Psychologist at Your Mind Matters. Blair supports clients with eating disorders and disordered eating, and is accredited through the NEDC to provide care in this area. Meet our team.

Book an appointment

The Craving Cycle: A CBT Concept for Managing Addiction

The edge of a spent wave on wet sand, with a breaking wave and a lone figure standing at the water’s edge behind

In psychological therapy, we’re almost always looking to make progress. This often comes back to behaviour change – i.e., how we’ll behave differently in the face of difficult situations and feelings. In therapy targeting addiction, our behavioural goal is basic but difficult – we want to cease the addictive behaviour causing us harm.

If you’re someone who struggles with addiction, Cognitive Behavioural Therapy (CBT) is one of a host of different treatments that can help you recover. CBT aims to a) provide education about the various thoughts, feelings, and behaviours that maintain addiction, b) devise tailored strategies for encountering addiction-related thoughts and feelings, and c) making meaningful changes to behaviour to reduce or cease the cycle of addiction.

This blog will be talking about The Craving Cycle – one of the most fundamental concepts in CBT for addiction. As it applies to a whole range of different addictions – including drugs, alcohol, gambling and food – we’ll refer to all of these things generically as the ‘addictive object’.

What is craving?

Craving is the physiological and psychological response to our addiction-related triggers. Triggers can be external (e.g., people, places, things, situations) or internal (e.g., thoughts, memories, images, feelings).

In CBT, we consider a craving any response that increases your motivation to engage in addictive behaviour. It could be an overwhelming sense of stress, intolerable anxiety, or just an irresistible pull towards whatever we’re craving. Understandably, we become motivated to ‘dampen’ these feelings by using the addictive object.

For better or worse, our choice to engage in the addictive object has consequences. The Craving Cycle is called a ‘Cycle’ for a reason – the more we use an addictive object to dampen our cravings, the more frequent and intense our cravings will become in response to our triggers. If we pull into the McDonald’s drive-thru every night after work, we’re only going to become more and more stimulated when we see those golden arches!

We often think of craving as a ‘wave’ – and on a graph of time vs. intensity, it literally looks like one.

Image source: Greater Geelong Psychology Clinic: Surfing your way to new habits

The fact a craving looks like a wave – i.e., reaches its intensity slowly and then dissipates quickly – leads us to call a key CBT strategy ‘urge surfing’. In urge surfing, we are up-skilling ourselves in the ability to handle difficult craving-related feelings.

Diagram listing the four parts of the craving cycle: the trigger, the addiction-related thought, the craving itself and the choice to use

What is the Craving Cycle?

The Craving Cycle is understood as having four component parts:

  • The trigger
  • The addiction-related thought or thoughts – thoughts that justify using the addictive object
  • The craving itself
  • The choice to use

How can I better manage these cravings?

The first and most basic step is to, as much as possible, eliminate both a) triggers, and b) access to the addictive stimulus. Eliminating triggers can be easy in some cases (e.g., not driving past an outlet for the object) but harder for others (e.g., inevitable thoughts, memories, and feelings). This is why eliminating access is so critical – if we have access to the addictive object in our household, we’re vulnerable to lapsing if/when a craving arises.

When most people think about eliminating triggers and/or access, they can become pretty overwhelmed. Sometimes, it’s near-impossible to totally eliminate triggers or access. In those cases, it becomes critical to learn how to ‘urge surf’ and deal with the difficult thoughts and feelings associated with this. Once we have a tried-and-true strategy to manage these, the urge to use becomes less daunting. In CBT, urge surfing is one of the most important strategies you’ll learn.

The good news is that the more we crave without using the addictive object, the less intense and frequent our cravings become. Cravings are a ‘use it or lose it’ response – the less we give in to them, the less likely they are to return. For this progress to be consistent, though, our behaviour also needs to be consistent. Lapses and relapses, no matter how short, can bring our cravings roaring back.

If you’re looking for some individualised and structured support, and want to start beating your cravings, the team at Your Mind Matters can help. Give us a call to book in an initial consult, and make mention if addiction is a particular concern for you.

There are also support groups available in the community (such as SMART Recovery and various Twelve Step programs) that can make recovery a less lonely experience. Lots of self-help resources can be found online, and online and telephone support services are listed below:

  • Alcohol and Drug Counselling Online
  • Positive Choices – drug and alcohol information
  • Family Drug Support: 1300 368 186
  • Gambling Help Line: 1800 858 858
  • DirectLine, Victorian alcohol and drug counselling: 1800 888 236
  • Lived Experience Telephone Support Service (LETSS), South Australia: 1800 013 755

More support options are listed on our resources page.

Diagram with three steps for managing cravings: eliminate the triggers, eliminate the access and learn to urge surf

References

Centre for Addiction and Mental Health. (2020). Cognitive behavioural therapy (CBT) for problem gambling. Centre for Addiction and Mental Health. Cognitive behavioural therapy for problem gambling

Fong, T. W. (2006). Understanding and managing compulsive sexual behaviours. Psychiatry (Edgmont), 3(11), 51-58.

Gonzales, M. (2020, February 27). What is Cognitive Behavioral Therapy (CBT)? DrugRehab. What is Cognitive Behavioral Therapy?

McHugh, R. K. (2010). Cognitive-Behavioral Therapy for Substance Use Disorders. Psychiatry Clinics of North America, 33(3), 511-525.

Naqvi, N. H. (2015). Cognitive regulation of craving in alcohol dependent and social drinkers. Alcohol: Clinical and Experimental Research, 39(2), 343-349.

National Institute of Clinical Excellence. (2011, February 23). Alcohol-use disorders: Diagnosis, assessment and management of harmful drinking (high-risk drinking) and alcohol dependence. National Institute of Clinical Excellence. NICE guideline CG115

Patrick Carey smiling outdoors, in a portrait photograph

Our Blog Author
This post was written by Patrick Carey, Clinical Psychologist at Your Mind Matters. Paddy works with adults presenting with anxiety and mood disorders, trauma, obsessive-compulsive disorders, substance and gambling issues, psychosis spectrum disorders, and grief and loss, and is trained in CBT, ACT, Cognitive Processing Therapy, Metacognitive Training and mindfulness approaches. Meet our team.

Book an appointment

How to Succeed in Achieving Your Goals: A Quick Guide to Changeology

A weathered mooring post in shallow water at sunset, with a two-masted sailing boat at anchor further out, out of focus

Photo by Annick Saminaden

“What you get by achieving your goals is not as important as what you become by achieving your goals.”

Henry David Thoreau

Change is a Process not a Single Event or Action

Humans are capable of impressive personal accomplishments even in the midst of deep suffering. The backbone of all goals is embracing self-change. Whether making a new habit stick (e.g., going to the gym) or making a permanent transformative life change (e.g., ending long-term addiction), navigating the process of change can be daunting.

The science of behaviour change (Changeology) outlines a more efficient and effective path to successful change and goal achievement, based on 40 years of extensive psychological research (Norcross, 2013).

“If you want to live a happy life, tie it to a goal, not to people or things.”

Albert Einstein

SMART Intrinsic Goals Provide Effective Direction to the New You

Define SMART goals to maximise your chances of success (Moore, 2019; Sutton 2020). Make your goals relevant to you and your life priorities. Intrinsic goals have deeply rooted personal meaning and align with our core values and need for growth and fulfilment. Meaning provides a sense of direction, purpose and satisfaction in life.

Specify realistic goals (and subgoals), differentiating between short-term and long-term goals. Ensure goals are within your control and are expressed in a healthy/positive direction. Measure your goals (e.g. number of cigarettes smoked) to track progress. Successful self-changers teach us that it takes 90 days to create lasting behaviour change (Norcross, 2013).

“ A goal without a plan is just a wish.”

Antoine de Saint-Exupéry

Stage of Change Predicts the Probability of Long-term Success

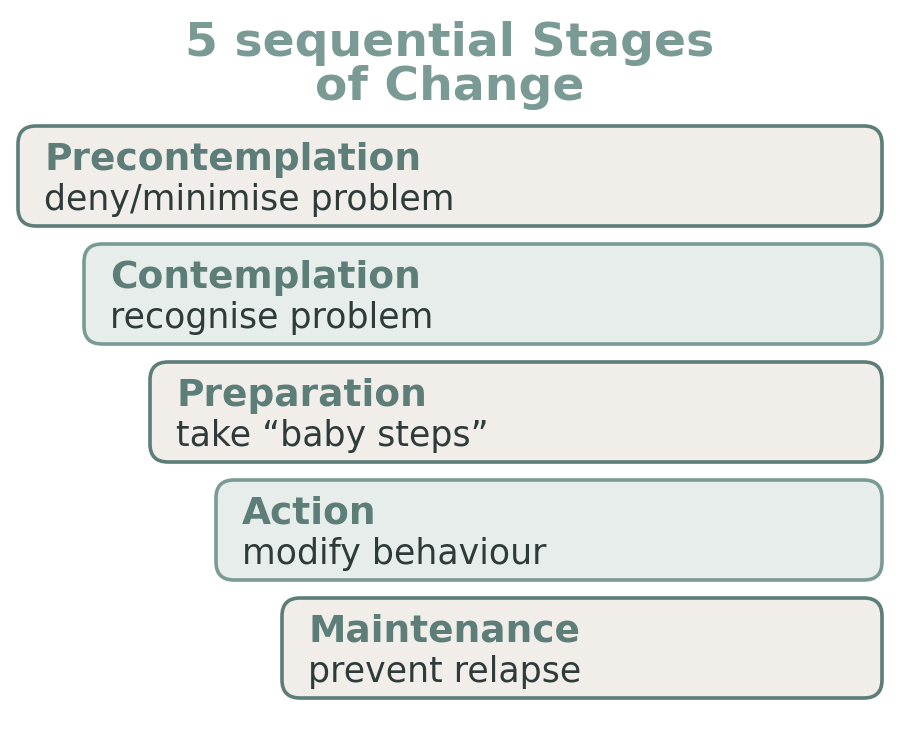
People’s journey of change typically unfolds over time across 5 sequential Stages:

  • Precontemplation (deny/minimise problem; no intention to change),
  • Contemplation (recognise problem; ambivalent about change; no commitment to act),
  • Preparation (intend to take action/ take “baby steps”),
  • Action (modify behaviour, experiences and/or environment to overcome problem),
  • Maintenance (prevent relapse and stabilise behaviour change over time).
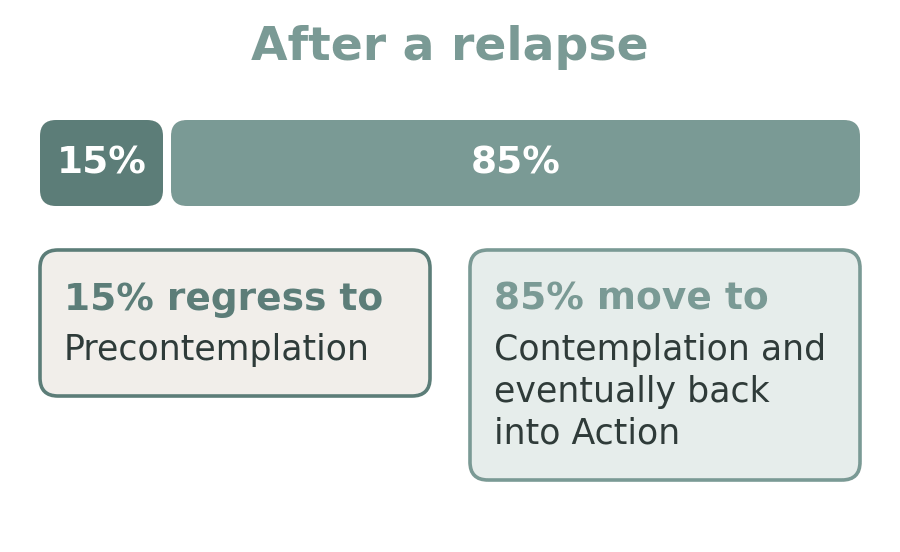
Diagram: after a relapse, 15% regress to Precontemplation and 85% move back to Contemplation and eventually into Action

People spend varying time in each stage, but complete specific activities at each stage to progress to the next stage (Transtheoretical Model). The further along you are in the stages, the more likely you are to succeed. Assess My State of Change (Dr John Norcross, ChangeologyBook.com) helps identify your readiness for change.

Diagram of the five sequential stages of change, from Precontemplation up to Maintenance

Key to Efficient Change and Goal Achievement: Doing the Right Thing at the Right Time

Dr Norcross’ scientific approach to realising goals involves traversing 5 sequential Steps over a period of 90 days. At every step, goal progression is tracked (e.g., graphing cigarettes smoked). This maintains focus, provides feedback and helps reward your achievement.

People derail at any step. Some remain in Contemplation confronted by unrealistic expectations/self-defeating thoughts. Others rely excessively on motivation/ willpower when needing skills to take Action. Research shows that 15% of individuals who relapse regress to Precontemplation while 85% move back to Contemplation and eventually back into Action. Moving from Contemplation to Action doubles a person’s chances of succeeding (e.g., sobriety).

Successful self-changers typically recycle through the Steps in a spiral path, before reaching their end goals and creating lasting change (e.g., maintaining sobriety). Focus on meaningful goals that place you further along in the 5 Steps process.

The key to success involves identifying your Step (stage) and implementing proven strategies/change catalysts specific to that Step, in order to move to the next Step (Step matching).

Norcross’ 5 Steps and Strategies to Achieving Your Goals:

1. Psych: Get Ready (Stage: Contemplation; Week 1&2)

Outline intrinsic goals and define the New You (without consequences of the problem behaviour). Increase motivation to change.

Catalysts: Raising awareness of problem behaviour/ (un)desirable consequences and (New) You. Harnessing emotions pulling you away from change/towards a better ideal future. Redirecting these emotions (e.g., fear/ guilt/ shame/regret) to propel you forward. Committing- reviewing Pros/Cons of change; declaring your goal to another person.

2. Prep: Prepare Before Leaping (Stage: Preparation; Week 2&3)

Define SMART Goals. Understand the behavioural chain of the problem behaviour (triggers /behaviour/consequences). Build commitment before making your goal public. Choose your start day, identify support people, take “baby steps” and prepare for the launch.

Catalysts: Committing (e.g., practicing healthy alternative behaviour to increase self-efficacy); Finalising Action Plan with your Change Team (1-4 committed/supportive people).

3. Perspire: Take Action (Stage: Action; Week 2-8)

Develop healthy alternatives to the problem and build new behaviours. Create a flourishing environment/Change Team.

Catalysts: Rewarding yourself for keeping on track. Countering (doing healthy opposites of the behavioural problem, e.g., confronting dreaded situations); Controlling your environment (e.g., avoiding high-risk situations/people that can rekindle problem behaviour); Maintaining contact with Change Team (e.g., to keep a positive outlook, cope ahead, practice skills-Saying NO to requests that regress to old behaviour).

4. Persevere: Manage Slips (Stage: Maintenance; Week 8-12)

Minimise exposure to triggers that precipitate a slip; Recognise a slip (lapse; single unwanted event) need not become a fall (relapse; end goal is abandoned /reverting back to old patterns); Forge towards your goal despite unavoidable self-defeating thoughts/feelings/setbacks. Reach out to your Change Team for support.

Catalysts: Responding constructively after a slip; Preparing for the next time you slip (Create My Slip Card; Dr John Norcross, ChangeologyBook.com).

5. Persist: Maintain Change (Stage: Maintenance; Week 12 and beyond)

Master relapse prevention skills to maintain the New You. Have backup plans for unavoidable slips. If a rare slip occurs, understand the behaviour/situation, and shift any self-blame to lessons learnt and respond constructively to steer yourself back on track towards your goal.

Catalysts: Sustaining new behaviour (value/intrinsic meaning act as reinforcer); Enhancing self-efficacy across high-risk situations; Understanding process of change; Distinguishing between when to exit or persevere for a lifetime. Exit if temptation to regress/relapse across triggers is very low, self-efficacy to maintain the new behaviour is high across situations and a healthy lifestyle precludes the old problem behaviour.

“ The journey of a thousand miles begins with one step.”

Lao Tzu

Persevere Towards Your Goals with One Small Step at a Time

Through the science of behaviour change, you understand why your efforts derail(ed) and how to steer yourself back on track towards successful goal achievement. You learn to celebrate progress, build self-efficacy and develop self-compassion. You also learn to harness emotions to turn your fears into fuel and feel empowered in your ability to make meaningful, lasting change.

Whatever unique goals or personal change you are seeking, our team of highly skilled mental health professionals at Your Mind Matters is here to support you.

Resources

Changeology Resources – Book, ChangeologyBook.com Free Resources, Podcast, Youtube

Norcross, J. C. (2013). Changeology: 5 Steps to realize your goals and resolutions. New York: Simon & Schuster.

Dr John Norcross- ChangeologyBook.com (e.g., Self-Assessments- Assess My State of Change, Self-Change Exercises-Create My Slip Card).

ChangeologyBook.com

Dr John Norcross – Proven Methods to Define Your Goals.

Proven Methods to Define Your Goals

Dr John Norcross – 5 Basic Steps of Change.

5 Basic Steps of Change

5 Stages of Change from the Transtheoretical Model.

5 Stages of Change from the Transtheoretical Model

Podcast- Dr John Norcross

How to Make Lasting Changes in Your Life with John Norcross.

How to Make Lasting Changes in Your Life

Goal Setting and Achieving Goals -Defining SMART Goals, Free Worksheets

Moore, C. (2019, May 27). How to Set and Achieve Life Goals The Right Way.

How to Set and Achieve Life Goals The Right Way

Sutton, Jeremy (2020, July 01). Goal-Setting: 20 Templates & Worksheets for Achieving Goals.

Goal-Setting: 20 Templates and Worksheets

Science behind Goals, Values, Meaning, Behaviour Change and Flourishing

Locke, E. A., & Latham, G. P. (2002). Building a practically useful theory of goal setting and task motivation: A 35-year odyssey. American Psychologist, 57(9), 705.

Maslow, A.H. (1943). A theory of human motivation. Psychological Review, 50(4), 370.

Prochaska, J. O., & DiClemente, C. C. (1982). Transtheoretical therapy: Toward a more integrative model of change. Psychotherapy: Theory, research & practice, 19 (3), 276-288.

Norcross, J. C., Mrykalo, M. S., & Blagys, M. D. (2002). Auld Lang Syne: Success predictors, change processes, and self-reported outcomes of New Year’s resolvers and nonresolvers. Journal of Clinical Psychology, 58(4), 397-405.

Norcross, J. C., Krebs, P. M., & Prochaska, J. O. (2011). Stages of change. Journal of Clinical Psychology, 67, 143-154.

Seligman, M. E. (2004). Authentic happiness: Using the new positive psychology to realize your potential for lasting fulfilment. Simon and Schuster.

Seligman, M. E. (2012). Flourish: A visionary New Understanding of Happiness and Well-being. Simon and Schuster.

Annick Saminaden smiling, in a portrait photograph

Our Blog Author
This post was written by Annick Saminaden, Senior Psychologist at Your Mind Matters. Annick works with young people and adults on stress, grief and loss, trauma, self-esteem, assertiveness and perfectionism, drawing on Cognitive Behaviour Therapy, Acceptance and Commitment Therapy, Dialectical Behaviour Therapy, Schema Therapy and Motivational Interviewing. Meet our team.

Book an appointment

Treating Obsessive-Compulsive Disorder

What is Obsessive-Compulsive Disorder (OCD)?

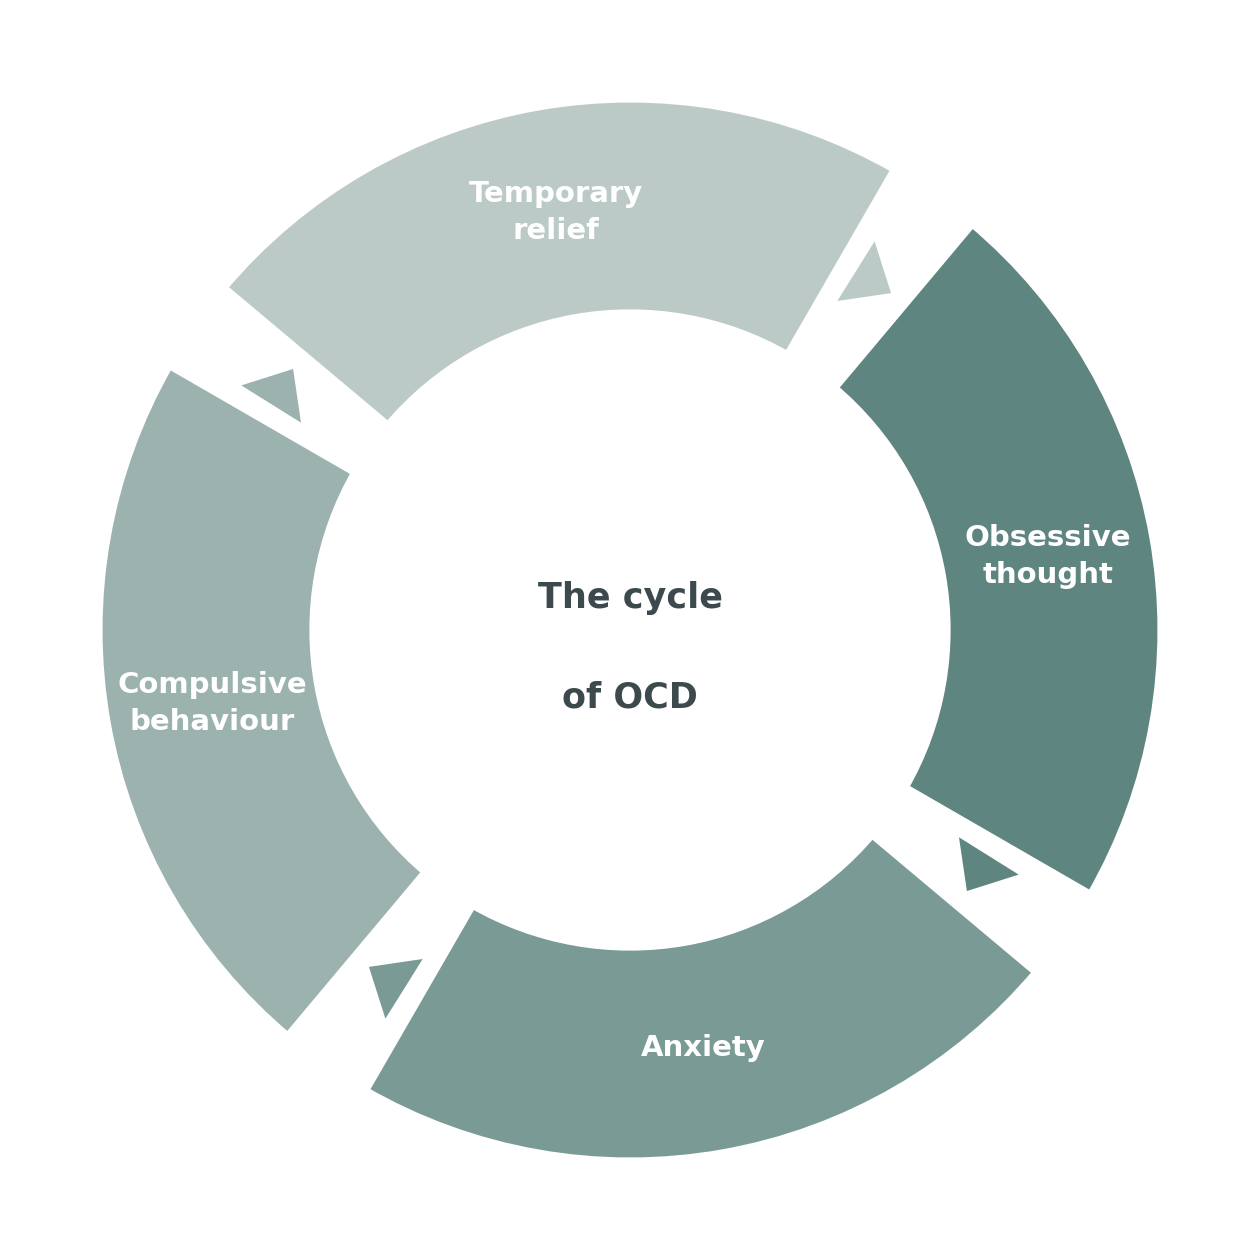
Diagram of the OCD cycle: obsessive thought leads to anxiety, then compulsive behaviour, then temporary relief, and back again

Maybe you’ve heard someone refer to themselves as having “OCD” or being “OCD” about certain things like cleanliness or orderliness. In reality, OCD is a mental illness that can dramatically impact someone’s life. OCD is characterised by the presence of intrusive and unwanted thoughts, ideas or images (obsessions) that lead to increased anxiety and repetitive, intentional rituals (compulsions) that are used to remove the anxiety. For more information relating to the understanding of OCD, check out our earlier blog here: Understanding Obsessive-Compulsive Disorder

Why does OCD occur?

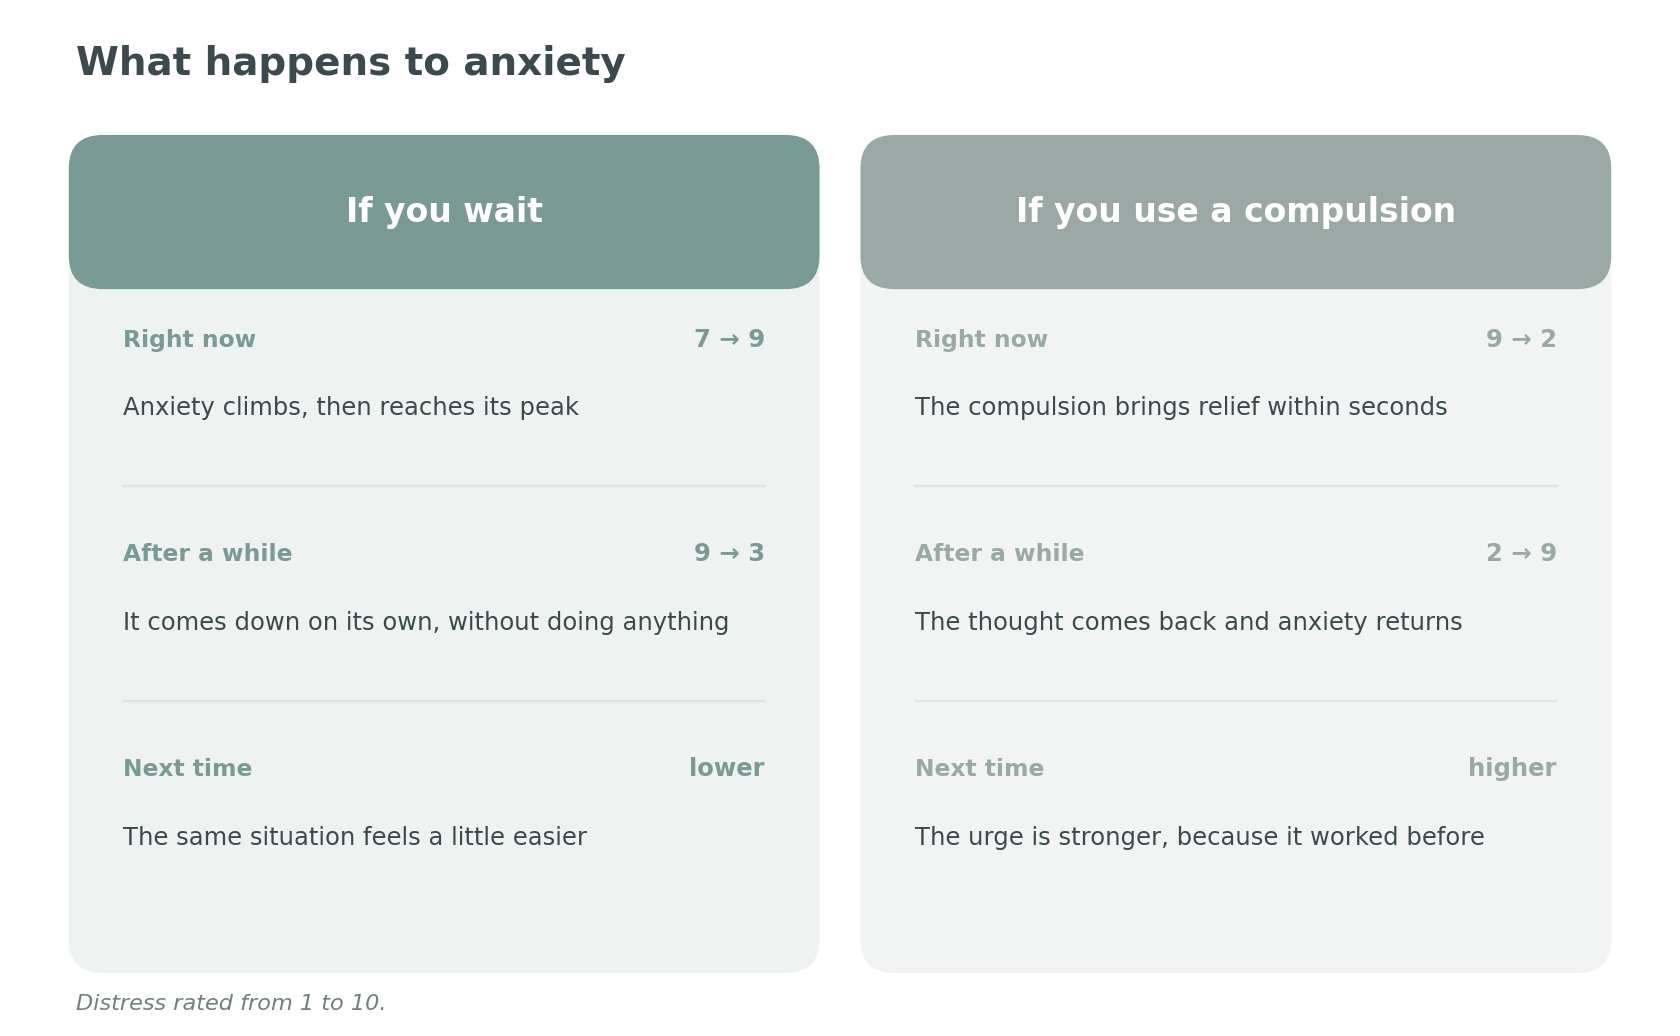
OCD tends to gradually build in severity due to the relationship that exists between the two factors, obsessions and compulsions. We are hardwired to attempt to solve problems with behavioural solutions, which for a long time in history that was integral! Thousands of years ago, we needed to effectively identify and avoid threats. If we didn’t feel the need to run away from a tiger hurdling towards us, we probably wouldn’t survive very long. In OCD, there is a miscalculation of a threat, where our obsessive, intrusive thought causes us undue anxiety. Often, we’re aware that these obsessions are irrational, yet we still have an urge to escape the “threat”. For example, someone with OCD may find themselves frequently thinking “If I forgot to turn the stove off, my house will burn down!” (obsession) feeling more and more anxious about it until they check to confirm they indeed have turned the stove off (compulsion). By checking, they have addressed the anxiety and the worry goes away until the obsession returns, which in some cases may be in a matter of minutes. In OCD, the person’s brain has LEARNT that the COMPULSION relieves ANXIETY and therefore wants to do it more!

How is OCD treated?

OCD can be a challenging condition to treat. Prolonged practice of challenging obsessions and confronting compulsions can assist in minimising the severity of OCD and can significantly improve wellbeing. When dealing with OCD, we want to focus on addressing both Obsessions and Compulsions, if we can find ways to disrupt both elements, we have two points of attack in challenging the OCD cycle.

Cognitive Behavioural Therapy (CBT) is a first-line recommended treatment for OCD. In CBT, we attempt to understand why the obsessions are occurring and why our brain has labelled them as “threatening”. During this process we also explore strategies that help us to minimise the use of compulsions, which are often the most impactful element of OCD. Often, this is done through something called exposure therapy.

Graded Exposure and Response Prevention Therapy for OCD

When entering a cold body of water, you might find it uncomfortable or difficult to stay in the water. However, after some time submerged, your body becomes used to the cold sensation and the water becomes much easier to tolerate. Much like cold water, the longer we can sit in the discomfort of anxiety without using compulsions to escape (i.e., get out of the water), the easier it gradually becomes.

Comparison of what happens to anxiety if you wait and if you use a compulsion, at the moment, after a while and next time

Graded Exposure and Response Prevention Therapy (ERP) is a process frequently used in addressing the compulsions of OCD. In this process, the client and the therapist work together to develop an exposure hierarchy, which is like a ladder of different experiences that are gradually more anxiety-provoking. After this, the client is exposed to each level of the ladder over a handful of sessions until each level feels manageable, gradually reaching the top of the ladder. In each instance, the job is to sit in the anxiety without using the compulsion to “escape” (or get out of the pool).

It’s a bit like weightlifting! If we want to lift 100kg and we’ve never touched a weight, it’s going to be very hard because we aren’t strong enough. But if we gradually increase the weight as we build up our strength, eventually we can lift the 100kg! The best thing about this process is that the task in front of us isn’t getting any harder because we are getting stronger. Similarly, our exposure hierarchy doesn’t tend to get much harder because we are building our tolerance to different situations.

ERP is super helpful in addressing compulsions but also facilitates challenging our anxious obsessions. Our anxious voice tells us that we have to use our compulsions in these situations, which we are able to challenge by showing ourselves that we can get through the discomfort without them.

Three steps for building an exposure hierarchy, with a scale of distress levels from one to ten

If you would like assistance addressing personal challenges in your own life related to OCD, why not give us a call? Our team of highly skilled and well-experienced psychologists are here to help. Call us now and take that first step towards obtaining the life you deserve!

References

Abramowitz, J. S., Deacon, B. J., & Whiteside, S. P. H. (2010). Exposure therapy for anxiety : Principles and practice. ProQuest Ebook Central ProQuest Ebook Central

Abramowitz, J. S. (2006). The psychological treatment of obsessive—compulsive disorder. The Canadian Journal of Psychiatry, 51(7), 407-416. doi: 10.1177/070674370605100702.

Hezel, D. M., & Simpson, H. B. (2019). Exposure and response prevention for obsessive- compulsive disorder: A review and new directions. Indian Journal of Psychiatry, 61(1), S85. doi:10.4103/psychiatry.IndianJPsychiatry_516_18

Steven Andritsos smiling in a portrait

Our Blog Author
This post was written by Steven Andritsos, Clinical Psychologist at Your Mind Matters. Steven works with teenagers and adults experiencing depression, anxiety, sleep disturbances and phobias, drawing on cognitive behavioural therapy alongside Dialectical Behaviour Therapy, mindfulness and Acceptance and Commitment Therapy. Meet our team.

Book an appointment

Couples conflict: Why do we keep hurting each other and fighting about the same thing?

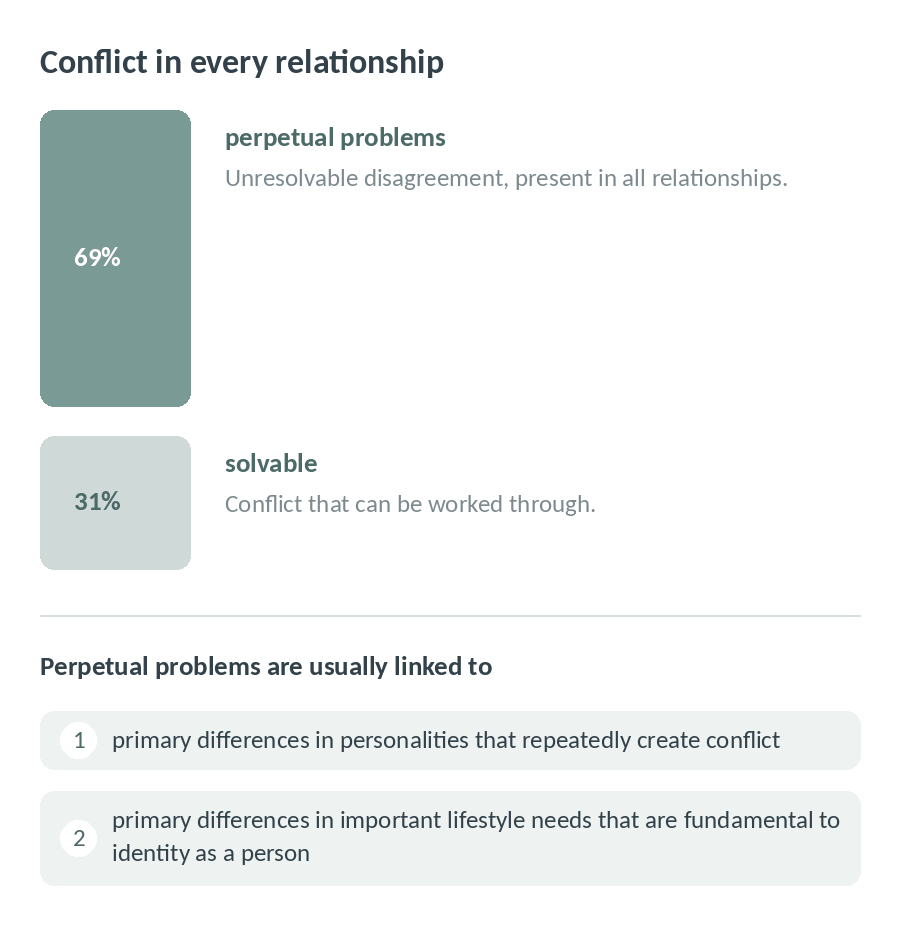
Conflict is a natural and unavoidable part of intimate relationships. Conflict often has a functional purpose and can actually provide opportunities for deeper connection and understanding. All relationships, even the most successful ones, have conflict. Gottman & Gottman’s longitudinal research on couples found that approximately 31% of couple conflict is solvable whilst 69% of disagreement in all relationships are associated with unresolvable perpetual problems. Perpetual problems are usually linked to 1) primary differences in personalities that repeatedly create conflict 2) primary differences in important lifestyle needs that are fundamental to identity as a person.

Examples of Perpetual Problems:

  • Differences in handling finances e.g.: one person has a philosophy of living in the now whilst the other is more conservative and wants to save for the future.
  • Differences in punctuality e.g.: one person is always late whilst the other likes to be on time.
  • Differences in organization and neatness e.g.: one person likes to keep an ordered clean house, the other is messy and disorganized.
  • Differences in how to raise and discipline children e.g.: one person is stricter and believes in consequences more than the other.
  • Differences in importance of social networks/people oriented e.g.: one person enjoys going out and is more gregarious or extraverted than the other.
  • Differences in independence e.g.: one person feels a greater need to be independent than the other.
  • Differences in sexual frequency e.g.: one person wants sex more than the other.

How can we manage conflict better?

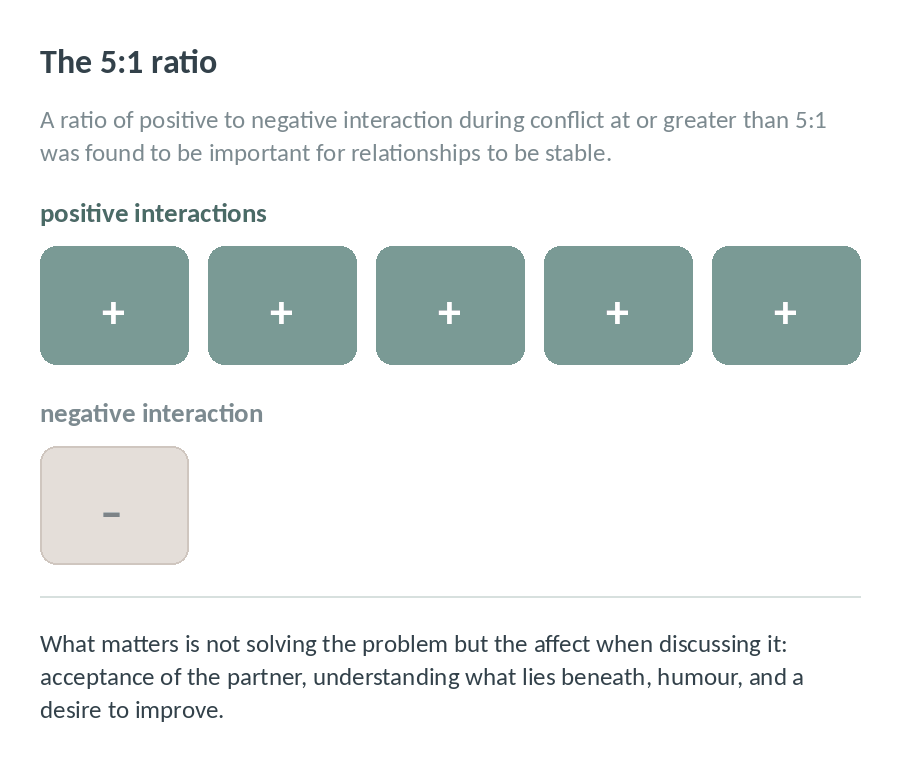
Research by Gottman & Gottman highlights that it is not the presence of conflict itself that is important, but how couples manage conflict through dialogue that predicts success or failure of a relationship. What we know by the research is that good relationships are characterized by respectful, “softened” dialogue, accepting influence, de-escalation of negativity, and bids for connection/repair attempts when things are good and also around these perpetual problems. What matters is not solving the problem but rather the affect when discussing the problem, acceptance of the partner, understanding what lies beneath, humour, and a desire to improve or actively cope with this perpetual problem. Importantly a positive effect and a ratio of positive to negative interaction during conflict being at or greater than 5 :1 was found to be important for relationships to be stable. Unfortunately, dysfunctional relationships may engage in conflict managing styles that insist on sides/winning. This is when the problem becomes gridlocked and we may experience feelings of hurt, sadness and loneliness. These painful exchanges often involve the four horsemen.

Sixty-nine per cent of couple conflict involves perpetual problems and thirty-one per cent is solvable
Five positive interactions alongside one negative interaction, the ratio associated with stable relationships

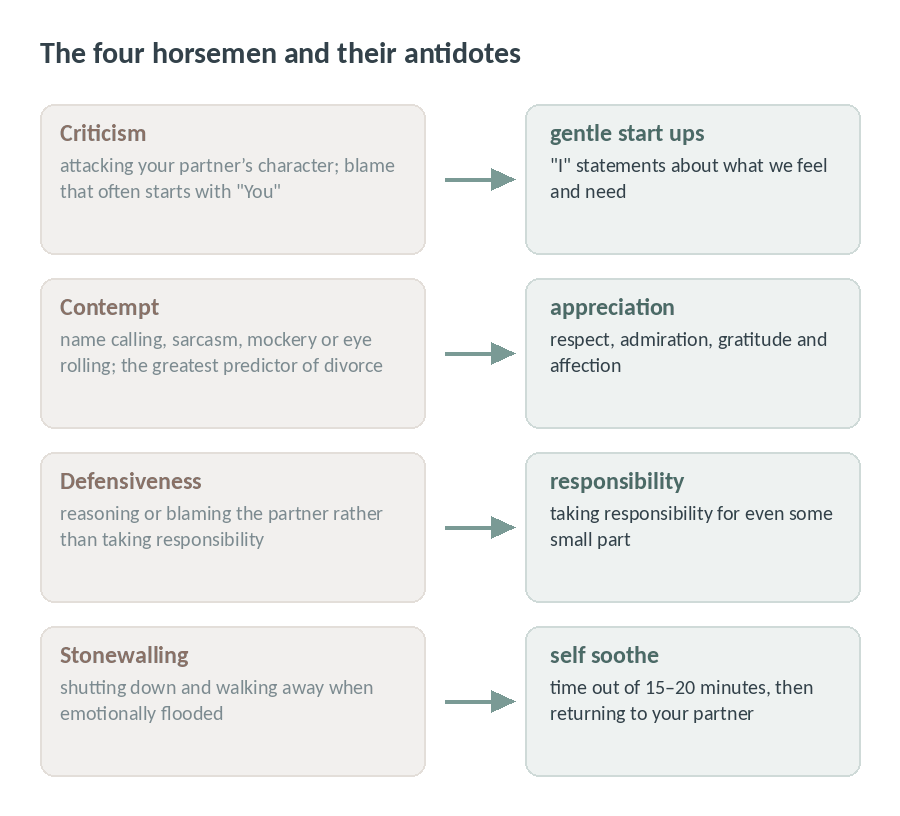
The Four Horsemen and their antidotes

Criticism

Do you sometimes attack your partner’s character? Sometimes we even “kitchen sink” the conversation whereby we pile another dirty dish of criticism into the conversation which adds to the negativity. Criticism involves blame and often starts with “You”. Using gentle start ups that involve “I” statements associated with what we feel (what emotion lies beneath this criticism?) and need is a way of still expressing our concerns, but without blame.

Example: Criticism – “Oh my god! You keep coming home so late. You are so selfish and inconsiderate”.
Antidote (gentle start up and stating positive need) – “ I feel so worried and stressed when you are home late. I love you and need you to let me know that you will be late”.

Contempt

Do you sometimes move to name calling, sarcasm, head shaking, mockery or eye rolling? Contempt is when we think we are morally superior and look down upon someone. Contempt is the greatest predictor of divorce. Building a culture of appreciation, respect, admiration, gratitude and affection in your relationship will help stop this negativity seeping into your relationship. Small positive interactions everyday help ward off contempt. Expressing understanding rather than contemptuous statements is important.

Example: Contempt – “You forgot to hang out the washing again this morning. Oh, congratulations baby! You are gold medal lazy” (says with eye roll)
Antidote (appreciation) – “I know and understand how busy with work you have been. I’d really appreciate it if you could remember to hang the washing before you leave”.

Defensiveness

Do you sometimes offer reasoning or even switch to blaming your partner rather than taking responsibility for your behaviour? Defensiveness is really about suggesting the problem isn’t you but them. It is a kind of self-righteousness and can also present as being the victim. By taking responsibility (for even some small part) we can manage this horseman and de-escalate things.

Example: Defensiveness – “ It’s not my fault I didn’t pick up takeaway on the way home even though I promised this morning. I’m busy! Get over it! Why didn’t you just do it!
Antidote (responsibility) – “Oh gosh, I am sorry I forgot the takeaway I promised to pick up. I should have actually asked you to grab it for us, because I knew I was going to be so busy at work. Sorry, that’s my fault. Let me call them now and order for us”.

Stonewalling

Do you sometimes shut down and walk away from a conflict? Stonewalling is often in response to our feelings of being overwhelmed or emotionally flooded. Diffuse physiological arousal can occur whereby heart beat increases, stress hormones are released and the fight or flight response is activated. Time out (approximately 15-20minutes) to self soothe (e.g.: deep breathing, listen to music) yet returning to your partner is the antidote.

Example: Stone walling – “You keep carrying on. There you go, over and over. Pathetic. There’s no point. I’ve had enough” (turns back on partner and leaves partner)
Antidote (self soothe) – “We aren’t getting anywhere on this at the moment and I’m sorry but I’m feeling really overwhelmed. Can I have a 20minute break and then come back to talk when I am calmer?”.

Help and support is available for couples at Your Mind Matters (YMM)!

If you are tired of getting into upsetting arguments with your partner and want some help learning to communicate without things getting gridlocked, why not call us today? Couples therapy at Your Mind Matters aims to help teach specific tools to enhance friendship, manage conflict, create shared meaning and in turn deepen intimacy in your relationship. We will work together in helping you identify your relationships strengths, its wounds, and ways to gently navigate the vulnerabilities.

Our team of highly skilled professionals are here to help. Call us now and take the first step in enriching your relationship and living a more fulfilled life.

References

Gottman J.M & Schwartz Gottman J, (2000-2016) Level 1 and 2 Clinical Training Manuals: Gottman Method Couples Therapy.

The four horsemen of criticism, contempt, defensiveness and stonewalling, each with its antidote
Your Mind Matters Psychology Services

Written by the team at Your Mind Matters
Our blog is written by the registered psychologists at Your Mind Matters Psychology Services in Notting Hill, Melbourne. If something here speaks to your situation, our team is here to help. Meet our team.

Book an appointment

Learning Assessments: What, When, Why and How?

A child’s backpack left on a chair in the waiting area of a psychology practice, with an adult and a child walking away down the corridor, out of focus

Has it been suggested that your child undergo a learning assessment? Are you unsure what a learning assessment involves or achieves? Your Mind Matters Psychology Services is here to help!

What are Learning Assessments?

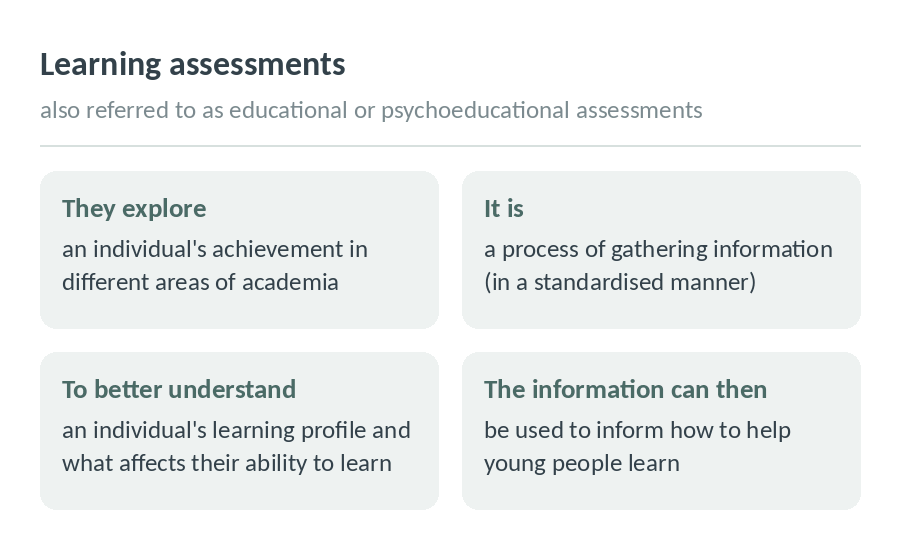
Learning assessments, also referred to as educational or psychoeducational assessments, are assessments that explore an individual’s achievement in different areas of academia. It is a process of gathering information (in a standardised manner) to better understand an individual’s learning profile and factors that may be affecting their ability to learn. This information can then be used to inform how to help young people learn and develop their skills to their full potential.

Diagram explaining what a learning assessment is: what it explores, how information is gathered, and what the results are used for
Numbered list of the benefits of a learning assessment, from understanding strengths and weaknesses to supporting self-esteem and confidence

When Should Learning Assessments be Completed?

There are many reasons why a learning assessment may be needed. Often, a teacher may recommend a learning assessment due to certain difficulties observed in a student’s academic performance. A paediatrician may refer a young person for a learning assessment because of behavioural concerns reported in the classroom. Parents/guardians may be querying why it is so difficult for their child to learn to read, write and/or complete maths problems. A young person may have concerns about their grades.

Ultimately, there is no ‘right’ time to undertake a learning assessment. However, the earlier difficulties can be identified, the earlier necessary supports can be put in place. Learning difficulties are associated with low self-esteem, and emotional and behavioural difficulties (Alesi, et al., 2014; Klassen et al., 2013). Therefore, earlier intervention can help mitigate these challenges and improve long-term outcomes for many individuals (Skues & Cunningham, 2011).

Why Undergo a Learning Assessment?

The benefits of completing a learning assessment can include:

  • Obtaining a better understanding of a young person’s cognitive and academic strengths and weaknesses.
  • Learning how to best support a young person’s learning through tailored strategies and recommendations.
  • Determining whether a young person has a learning disability, such as a Specific Learning Disorder (SLD) with impairment in reading (dyslexia), written expression (dysgraphia) and/or mathematics (dyscalculia).
  • Understanding if a young person is being academically challenged at school.
  • Making informed decisions regarding a young person’s education, including school placement and applying for special considerations (e.g., extra time on exams).
  • Supporting the development of a young person’s self-esteem and confidence by providing them with an opportunity to gain insight into their learning profile (and potential reasons behind their difficulties).

How are Learning Assessments Completed?

Learning assessments can vary depending on the individual, their needs and referral reason; however, the typical process includes:

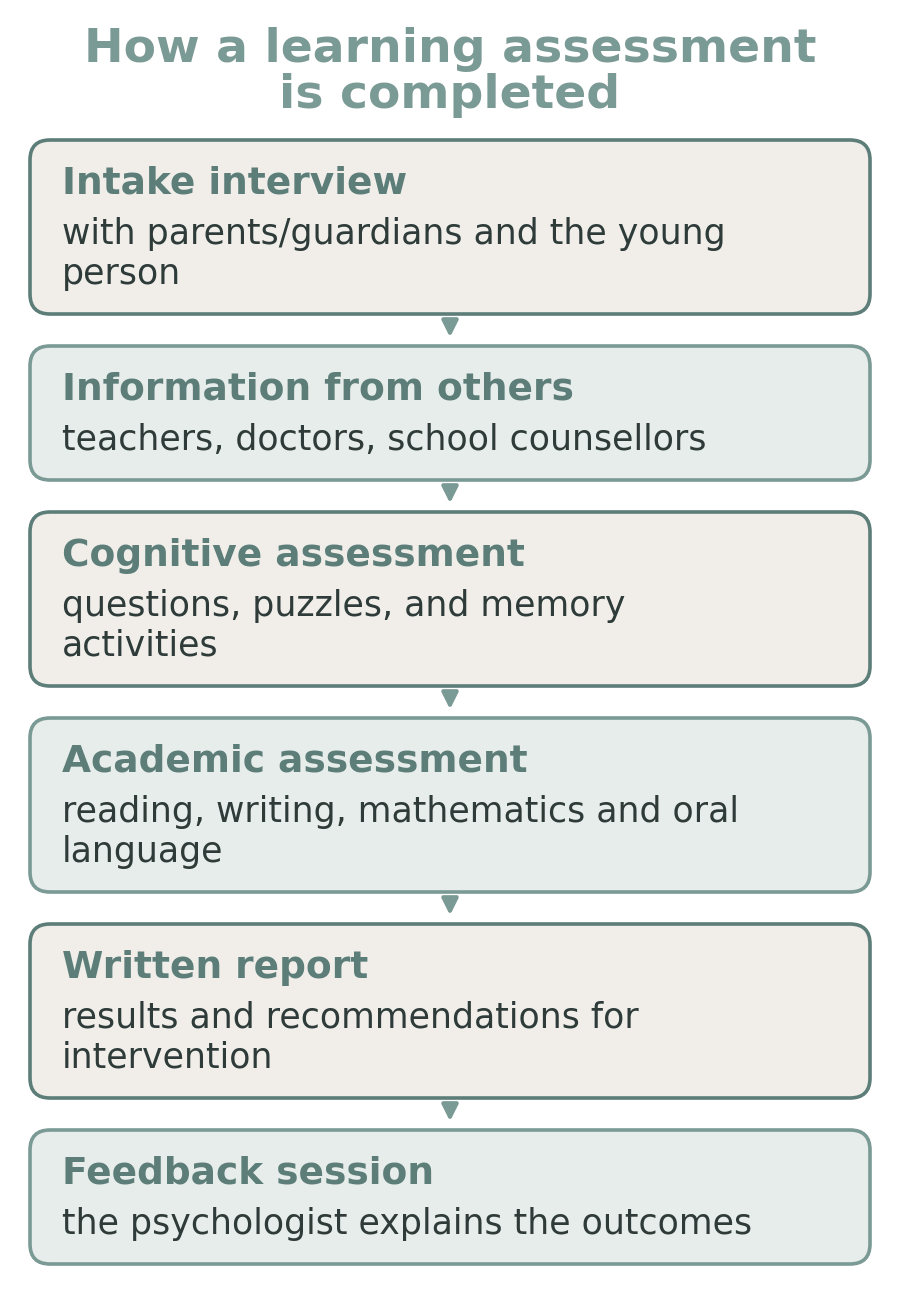
  1. An initial intake interview with parents/guardians and the young person (if appropriate), where detailed information about the young person’s development and learning history is gathered by the psychologist.
  2. The assessing psychologist may also want to collect information from other professionals involved in the young person’s care such as teachers, doctors, school counsellors, speech pathologists, etc., as this can help provide an understanding of the young person’s functioning in different environments.
  3. A cognitive assessment, where the young person works individually with the psychologist to complete a range of tasks, including questions, puzzles, and memory activities. This assessment will provide information about how the young person thinks, solves problems, processes information and remembers.
  4. An academic assessment, where the young person works individually with the psychologist to complete a range of reading, writing, mathematics and oral language tasks.
  5. A written report that includes all of the assessment results, as well as recommendations for intervention and/or support.
  6. A feedback session, whereby the psychologist will explain the outcomes of the assessment to the parents/guardians and young person (if appropriate). This session also provides clients with the opportunity to ask the psychologist any questions about the results or steps moving forward.

In addition to the assessment of cognitive and academic abilities, learning assessments at Your Mind Matters Psychology Services can also include the exploration of other factors related to learning such as attention, motivation, affect, and behaviour.

What now?

If you have queries or concerns regarding your child’s learning, or if you would like further information regarding learning assessments (including availability), please contact Your Mind Matters Psychology Services at (03) 9802 4654. Our team of psychologists are passionate about uncovering young people’s learning potential and discovering ways to help them achieve it!

References

Alesi, M., Rappo, G., & Pepi, A. (2014). Depression, anxiety at school and self-esteem in children with learning disabilities. Journal of psychological abnormalities, 1-8. https://doi.org/10.4172/2329-9525.1000125

Klassen, R., Tze, V., & Hannok, W. (2013). Internalizing Problems of Adults With Learning Disabilities. Journal of Learning Disabilities, 46(4), 317–327. https://doi.org/10.1177/0022219411422260

Skues, J., & Cunningham, E. (2011). A contemporary review of the definition, prevalence, identification and support of learning disabilities in Australian schools. Australian Journal of Learning Difficulties, 16(2), 159–180. https://doi.org/10.1080/19404158.2011.605154

Flow diagram of how a learning assessment is completed: intake interview, information from others, cognitive assessment, academic assessment, written report and feedback session
Your Mind Matters Psychology Services

Our Blog Author
This post was written by Tayla Chellew, formerly a Psychologist at Your Mind Matters. Learning assessments continue to be part of our assessment services. Meet our team.

Book an appointment

What is Play Therapy? And how can it help your child?

The children’s therapy room at Your Mind Matters, with an easel, a play kitchen and shelves of toys

“Enter into children’s play and you will find the place where their minds, hearts, and souls meet.” -Virginia Axline

What is Play Therapy?

Play Therapy is an effective and appropriate way to help children aged 2-12 years work through emotional, psychosocial and behavioural difficulties. It can help address issues faced in the family, school, or interpersonal relationships. This technique works for children like counselling or psychotherapy does for adults.

Play Therapy is based upon the fact that play is the child’s natural medium of self-expression. In Play Therapy a child is given the opportunity to ‘play out’ feelings and problems just as an individual in adult therapy may ‘talk out’ their difficulties.

The child therapy room at Your Mind Matters in Notting Hill, with a small table, an easel, a bean bag and an armchair

In Play Therapy, a relationship develops between the child and the therapist, where the therapist enters the child’s world, following the child’s lead, to develop a safe place and a relationship of trust, empathy and acceptance. Within this context, children are then free to express feelings, thoughts, experiences, and behaviours through play. Toys are used like words and become the child’s natural language. Children are encouraged to make choices, to explore possibilities and to develop resilience and self-actualisation, with a skilful therapist trained to respond therapeutically.

Who Play Therapy is for: children aged two to twelve facing difficulties such as trauma, grief, anxiety and family change

Who is Play Therapy for?

Play Therapy can assist children aged 2-12 years experiencing difficulties such as:

  • Child abuse and neglect
  • Developmental trauma
  • Grief and loss
  • Relationship and social issues
  • Adjusting to family changes such as separation and divorce
  • Social issues – difficulties with friendships, social skills
  • Emotional regulation issues
  • Anxiety
  • Selective mutism
  • Chronic illness or medical trauma

Benefits of Play Therapy

Play Therapy provides a safe and therapeutic environment for children to explore and learn about themselves and their world, to build confidence and self-esteem, whilst working through the issues that may have hindered their development so far.

Play Therapy helps children to find healthier ways of communicating and to develop a greater sense of identity and self-esteem, while increasing their emotional intelligence and resilience.

Evidence based literature supports the effectiveness of play therapy, with research replicated with different cultural groups and demographics.

Shelves of toys, a play kitchen and dolls houses in the children’s room at Your Mind Matters

History and adaptations of Play Therapy

Virginia Axline originally developed Child-Centred Play Therapy as a methodology based on key principles of the person-centred approach, with primary focus on the relationship between child and therapist being based on genuineness, acceptance and trust. This created a safe and trusting environment for children to explore and examine all emotions and experiences at their own pace, and to integrate them. The therapist works with the child to provide empathy and unconditional acceptance, to help the child to feel understood, so they in turn can gain a sense of mastery and understanding of their own experiences.

In the 1960s, Bernard and Louise Guerney developed Filial Therapy, an adaptation of Play Therapy where parents were taught Child-Centred Play Therapy skills so that they could facilitate therapy sessions with their children. This model recognised the influential impact of parents in assisting their children’s healing and growth. Landreth refined this model into a 10-session structured program known as Child-Parent Relationship Therapy, an evidence-based model focused on strengthening the parent–child relationship and helping parents to better understand and respond to their children’s social, emotional, and behavioural needs.

Modern day Play Therapy incorporates many different methodologies adapted to the child’s age and stage of development, presenting issues, and stage of therapy. These can often incorporate structured or unstructured play, storytelling, art techniques, games and sand tray. The goal is still to provide an accepting and open environment for a child to feel safe to express their feelings, but techniques may utilise directive strategies as well.

If you would like to learn more about play therapy and how your child can benefit from this counselling approach, our team of clinicians can help.

If you or your child need support right now

If this is an emergency, call 000. Kids Helpline is available on 1800 55 1800 for children and young people aged 5 to 25, and Lifeline on 13 11 14 or text 0477 13 11 14, both 24 hours a day. More options are on our resources page.

References

Axline, V. (1967; republished 1989). Play therapy: The inner dynamics of childhood. New York: Ballantine Books.

Bratton, S. C., Landreth, G. L., Kellam, T., & Blackard, S. R. (2006). Child parent relationship therapy (CPRT) treatment manual: A 10-session filial therapy model for training parents. Routledge/Taylor & Francis Group.

Cochran, N. H., Nordling, W. J. & Cochran, J. L. (2010). Child-centered play therapy: A practical guide to developing therapeutic relationships with children. New Jersey: John Wiley & Sons.

Landreth, G. L. (2012). Play therapy: The art of the relationship. New York: Routledge.

Your Mind Matters Psychology Services

Our Blog Author
This post was written by Shivonne Cammell, formerly a Senior Accredited Mental Health Social Worker at Your Mind Matters. Play therapy continues to be part of our services for children. Meet our team.
Book an appointment
📅 Book an Appointment